
Prolapse or Laxity? Knowing Which Specialist You Actually Need
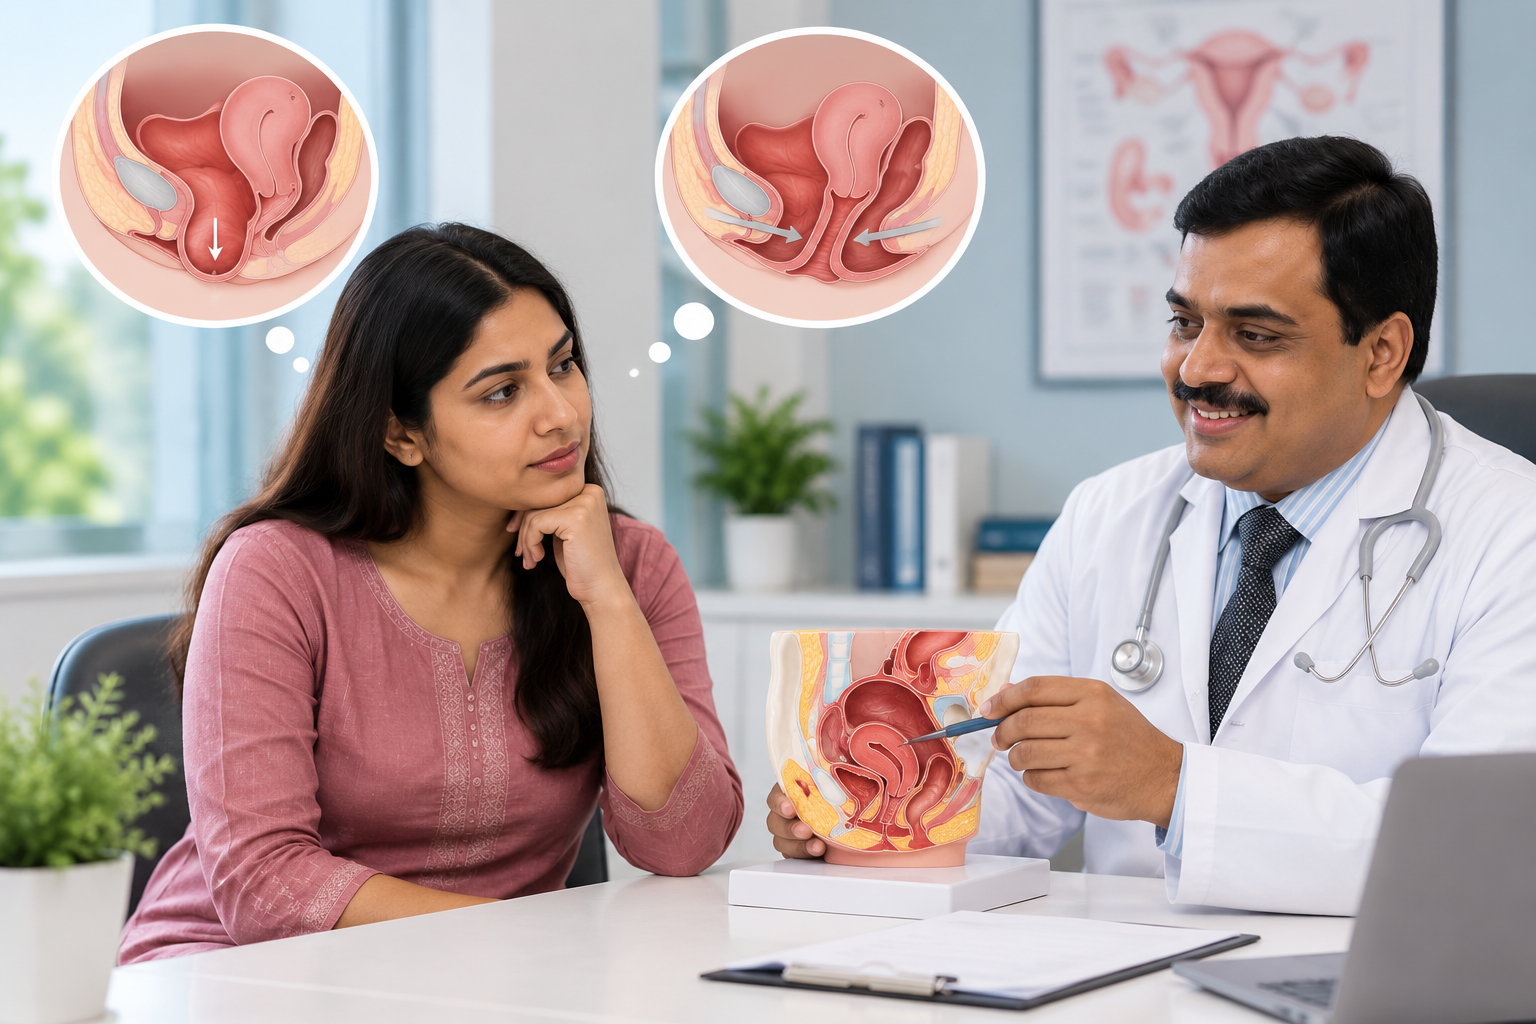
Laxity is a loss of tone and snugness in the vaginal walls, while prolapse is descent of the uterus, bladder or bowel into or toward the vagina. Understanding the difference between prolapse and vaginal laxity matters because prolapse requires gynaecological assessment and management rather than simply choosing a cosmetic vaginal tightening procedure.
Laxity is a loss of tone and snugness in the vaginal walls, while prolapse is descent of the uterus, bladder or bowel into or toward the vagina. Understanding the difference between prolapse and vaginal laxity matters because prolapse requires gynaecological assessment and management rather than simply choosing a cosmetic vaginal tightening procedure.
After childbirth or with age, some women notice a feeling of looseness, pelvic heaviness, pressure or something “coming down.” These symptoms can sound similar, but they do not necessarily represent the same condition.
The difference between prolapse and vaginal laxity is important because the underlying structures involved, examination findings and appropriate treatment are different.
Vaginal laxity generally describes reduced tone or a subjective feeling of looseness. Pelvic organ prolapse occurs when pelvic support weakens enough for an organ such as the bladder, uterus or rectum to descend toward or into the vagina.
If you are unsure which problem you have, an examination is more useful than choosing a treatment based only on symptoms.
For related information, see Vaginal laxity after childbirth.
What does laxity feel like and what does prolapse feel like?
Symptoms can overlap, which is why self-diagnosis can be difficult.
What vaginal laxity may feel like
Vaginal laxity is usually described as a change in vaginal tone or sensation.
A person may notice:
- A feeling of increased looseness
- Reduced sensation of vaginal tightness
- Changes noticed after vaginal delivery
- Reduced pelvic floor support
- Changes during intimacy
- Difficulty engaging the pelvic floor muscles
Laxity does not necessarily mean an organ is descending into the vagina.
Some symptoms attributed to “looseness” may also be related to pelvic floor muscle weakness rather than stretched vaginal tissue itself.
What prolapse may feel like
Pelvic organ prolapse can produce a different pattern.
Possible symptoms include:
- Pelvic pressure or heaviness
- A dragging sensation
- Feeling that something is coming down
- A bulge at or near the vaginal opening
- Symptoms becoming more noticeable after prolonged standing
- Bladder or bowel symptoms in some patients
- Difficulty emptying the bladder or bowel in certain cases
The symptoms depend partly on which pelvic structure is affected and how significant the descent is.
A feeling of heaviness does not prove that prolapse is present, but it is a reason to have the pelvic support structures assessed.
Why symptoms alone are not enough
Someone with mild prolapse may have relatively few symptoms, while another person with pelvic floor weakness but no significant organ descent may feel considerable discomfort.
That is why the difference between prolapse and vaginal laxity is established through history and examination rather than symptoms alone.
How is prolapse graded on examination?
Pelvic organ prolapse is assessed during a pelvic examination.
The clinician looks at which compartment is descending and how far that descent extends.
Depending on the individual case, the examination may assess the:
- Anterior vaginal wall and bladder support
- Uterus or vaginal apex
- Posterior vaginal wall and rectal support
- Pelvic floor muscles
- Vaginal tissue
- Perineal support
The patient may sometimes be asked to bear down or cough so that the degree of descent becomes easier to assess.
What does grading mean?
Clinicians may document prolapse using a recognised staging or measurement system. One commonly used approach is the Pelvic Organ Prolapse Quantification system, often called POP-Q.
Rather than relying on the patient simply being told that the prolapse is “small” or “large,” structured assessment helps document where the organs sit in relation to the vaginal opening.
The stage alone does not decide treatment. Symptoms, age, general health, future pregnancy plans, urinary or bowel problems and the patient's own treatment priorities also matter.
Why is a cosmetic tightening procedure the wrong answer for prolapse?
A vaginal tightening treatment and prolapse treatment are intended to address different anatomical problems.
If an organ is descending because its supporting structures have weakened, simply trying to make the vaginal opening or walls feel tighter does not necessarily correct that loss of support.
This is one of the most important reasons to establish the diagnosis before selecting a procedure.
Tightness is not the same as support
A patient may describe both conditions as “loose,” but clinically they are not interchangeable.
A cosmetic procedure aimed at vaginal laxity does not automatically restore the supporting structures responsible for bladder, uterine or bowel prolapse.
Prolapse does not always require surgery either
Being diagnosed with prolapse does not automatically mean an operation is required.
Depending on the type, severity and symptoms, management may include observation, pelvic floor rehabilitation, lifestyle measures, a vaginal pessary or surgery.
The appropriate option should follow a proper gynaecological assessment.
For related safety considerations before choosing an intimate procedure, read Is cosmetic gynaecology safe?.
How does referral usually work between gynaecology services and specialist centres?
The correct starting point depends on the symptoms and examination findings.
If symptoms suggest prolapse—particularly a vaginal bulge, significant pelvic pressure, urinary difficulties or bowel symptoms—a gynaecological or pelvic-floor assessment is appropriate.
If the main concern is vaginal laxity without organ descent, the assessment can focus more specifically on pelvic floor strength, tissue laxity and whether conservative management should be tried before discussing a procedure.
What if you first attend an intimate wellness clinic?
An appropriate assessment should identify when symptoms fall outside the scope of a cosmetic treatment.
If prolapse is suspected, the patient should be directed toward appropriate gynaecological evaluation rather than simply being offered tightening treatment.
Likewise, a patient who has already been assessed by a gynaecologist but remains concerned about laxity may later discuss whether another specialist assessment is appropriate.
This referral process helps ensure that the diagnosis not the treatment being advertised—determines the next step.
Which investigations are done before any procedure is planned?
Not every patient needs scans or complex testing.
The starting point is usually a detailed history and examination.
Medical and obstetric history
The clinician may ask about:
- Number and type of deliveries
- Difficult or assisted births
- Previous pelvic surgery
- Menopause
- Urinary leakage
- Difficulty emptying the bladder
- Constipation or bowel symptoms
- Pelvic pressure
- Sexual symptoms
- Future pregnancy plans
These details can help distinguish between muscular weakness, tissue laxity and possible pelvic organ prolapse.
Pelvic examination
The examination assesses tissue quality, vaginal support, pelvic floor function and whether an organ descends when pressure increases.
A proper examination is especially important before considering any procedure for presumed laxity.
Urinary assessment when indicated
If urinary leakage is also present, additional assessment may be appropriate because stress urinary incontinence can coexist with pelvic floor weakness or prolapse.
Read more about Stress incontinence treatment in Surat.
Additional testing
Ultrasound, bladder investigations or other tests may be considered when the symptoms or examination indicate a need. They are not automatically necessary for every person reporting laxity.
Before considering an elective intimate procedure, patients can also review Who is a candidate.
What happens when both are present together?
Vaginal laxity and pelvic organ prolapse are not mutually exclusive.
A person can have reduced vaginal tone as well as weakness of the structures supporting the bladder, uterus or bowel.
This makes diagnosis particularly important.
Treat the functional problem first
When clinically significant prolapse is present, treatment planning should first address the support problem and the symptoms it is causing.
A separate concern about laxity can then be considered within that wider treatment plan.
Pelvic floor weakness may contribute to both
Pregnancy, childbirth, ageing and other factors can affect the pelvic floor.
Some patients may therefore benefit from pelvic floor rehabilitation regardless of whether further treatment is eventually required.
One procedure should not automatically be expected to solve everything
A treatment aimed at one anatomical problem may not correct another.
Patients should understand exactly:
- Which diagnosis has been made
- Which structure is being treated
- What symptoms treatment is intended to improve
- Which symptoms may remain
- What alternatives are available
This avoids treating every postpartum pelvic symptom as a cosmetic “tightness” problem.
Prolapse vs Vaginal Laxity: How to Tell the Difference
| Symptom / Finding | Likely Possibility | Examination Finding | Appropriate Specialist | First-Line Management |
|---|---|---|---|---|
| Feeling less snug after childbirth | Vaginal laxity or pelvic floor weakness | Reduced tone without significant organ descent | Gynaecology/pelvic floor or appropriate intimate wellness assessment | Pelvic floor assessment and conservative management where appropriate |
| Pelvic heaviness or dragging | Possible prolapse | Descent may be seen during examination | Gynaecologist / pelvic-floor specialist | Examination followed by treatment according to type and symptoms |
| Something feels as though it is coming down | Prolapse should be excluded | Vaginal wall, uterus or apex may descend | Gynaecologist / urogynecology where appropriate | Assessment; conservative or surgical options according to findings |
| Visible or palpable vaginal bulge | More suggestive of prolapse | Organ/supporting wall descends toward or beyond vaginal opening | Gynaecologist / urogynecologist | Depends on symptoms and prolapse severity |
| Reduced pelvic floor contraction | Pelvic floor weakness | Weak muscle contraction on examination | Pelvic floor physiotherapist / gynaecology | Supervised pelvic floor rehabilitation |
| Urinary leakage with coughing or exercise | Stress urinary incontinence may coexist | Examination and urinary assessment as indicated | Gynaecology / urogynecology | Pelvic floor therapy and further treatment according to severity |
| Laxity plus confirmed organ descent | Both may coexist | Reduced tone plus prolapse findings | Gynaecological assessment first | Treat according to the functional diagnosis and overall findings |
Conclusion
Understanding the difference between prolapse and vaginal laxity prevents two different problems from being treated as though they were the same.
Vaginal laxity generally relates to reduced tone or a feeling of looseness, while prolapse involves descent of pelvic organs or their supporting vaginal walls. Because symptoms can overlap, examination should come before choosing treatment.
A tightening procedure should not be used as a substitute for appropriate prolapse management. When both conditions coexist, the treatment plan should address the functional pelvic-support problem and then consider any remaining laxity concerns.
Have a Private Question?
Every concern deserves an honest answer. Book a confidential consultation with Dr. Ashutosh Shah at Elegance Clinic, Surat, for guidance made just for you.

About the Author
Dr. Ashutosh Shah is a cosmetic gynecologist and plastic surgeon with over 22 years of experience. At Elegance Clinic in Surat, he is known for safe, honest and completely confidential intimate and aesthetic care.
Is a heaviness or dragging sensation a sign of prolapse?
It can be. Pelvic heaviness or a dragging sensation is associated with prolapse, especially when accompanied by a bulge or “something coming down” feeling. An examination is needed because other pelvic conditions can produce similar symptoms.
Can a tightening procedure correct prolapse?
A cosmetic tightening procedure should not be assumed to correct pelvic organ prolapse. Prolapse involves loss of organ support and requires proper gynaecological assessment so treatment can address the structures actually involved.
Which examination confirms the diagnosis?
A pelvic examination is usually central to diagnosing prolapse. The clinician assesses vaginal support and may ask you to bear down so the position of the bladder, uterus, vaginal walls and other structures can be evaluated.
Does prolapse always need surgery?
No. Treatment depends on symptoms, type and severity. Some patients may be managed with observation, pelvic floor rehabilitation, lifestyle measures or a pessary, while surgery is considered when appropriate.
Can prolapse appear years after delivery?
Yes. Pelvic support changes associated with pregnancy and childbirth may become more noticeable later, and ageing or menopause can also affect pelvic tissues.
Who should I see first if I am not sure?
If you have heaviness, a vaginal bulge, bladder or bowel symptoms, or a “something coming down” sensation, start with a gynaecological assessment.