What is latissimus dorsi flap phalloplasty?
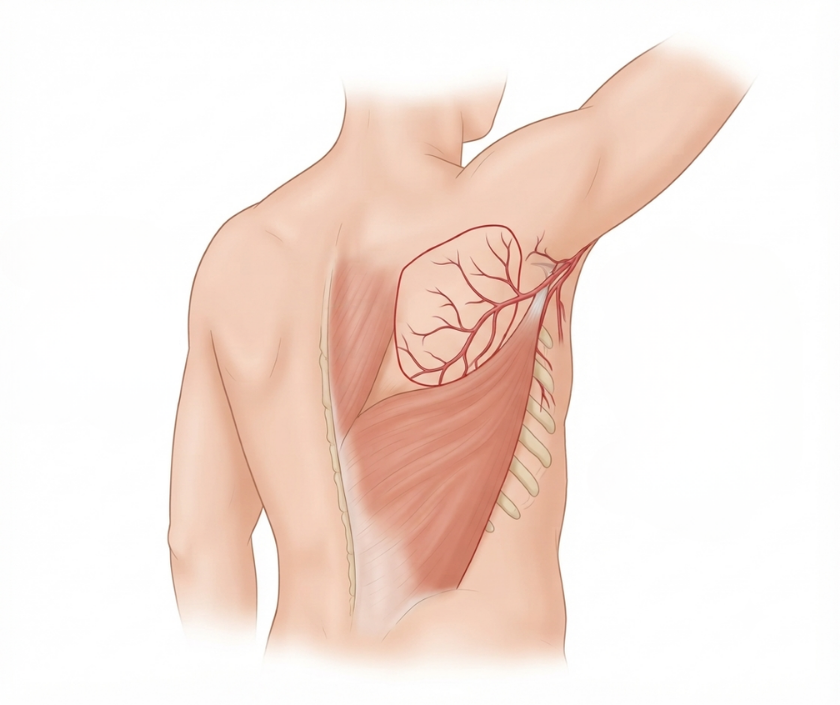
Latissimus Dorsi Flap Phalloplasty builds a phallus using skin and muscle taken from the back. Rather than one operation, it is a staged reconstruction carried out over time. In the first stage, the flap is raised, shaped, and joined to blood vessels and nerves at the groin. Because the back can supply generous tissue, this flap suits some people well. Through later stages, the urethra and an implant are added.
Who might consider this flap?
People who consider this flap often want good bulk and a donor site that hides under clothing. Because the back scar sits where a shirt covers it, some prefer it to a forearm scar. For others, arm or thigh flaps suit better. Good general health, healthy blood vessels, and realistic expectations all matter. Above all, the surgeon advises honestly whether this option fits you.
How does it compare to other flap choices?
It compares to forearm and thigh flaps mainly in bulk, sensation, and scar position. Whereas a forearm flap is thinner with strong sensation potential, the back flap offers more bulk. Because the back has fewer sensory nerves to borrow, feeling may differ. Meanwhile, the donor scar is easier to hide. As a result, the choice balances sensation, bulk, and scarring for you.
How is the surgery performed?
The surgery is performed in stages under general anaesthesia. First, the surgeon raises the flap of skin and muscle from the back. Next, the flap is shaped into a phallus and moved to the groin. After that, its blood vessels and nerves are joined with fine, careful stitches. Because blood supply is critical, the flap is watched closely afterwards. Finally, later stages add the urethra and an implant.
Is this surgery done in stages?
Yes, Latissimus Dorsi Flap Phalloplasty is staged over more than one operation.
- Stage one builds and connects the phallus
- A later stage lengthens the urethra where planned
- A further stage adds a stiffening implant
Because each stage needs full healing first, the whole process can take a year or more. Meanwhile, the team plans the timeline honestly with you.
What are the risks and complications?
This is complex, high risk surgery, so the risks are named plainly.
- Partial or total flap loss if blood supply fails
- Urethral fistula and stricture, which are common
- Bleeding, infection, or delayed healing
- Donor site scarring and shoulder weakness
- Implant problems needing revision
- Reduced or altered sensation
Because these problems are real, the team discusses each one honestly before you decide.
Will I be able to pass urine standing?
Passing urine standing is possible only if urethral lengthening succeeds, which is not guaranteed. Because the new urethra is long and complex, fistula and stricture are common. For this reason, some people choose not to lengthen the urethra at all. Meanwhile, staged repair can often fix problems that arise. The team explains these honest limits before surgery.
What sensation can I expect?
Sensation depends on how well nerves connect and recover, and it develops slowly. Because the flap is joined to groin nerves, protective feeling often returns over months. Still, erotic sensation is less predictable and may be reduced. Meanwhile, the clitoral tissue is usually kept for sensation. The team is honest that outcomes differ and cannot be guaranteed.
How is the flap monitored after surgery?
The flap is monitored very closely in the first days, since early problems must be caught fast. Because blood supply can fail suddenly, nurses check colour, warmth, and flow often. For this reason, the early hospital stay is longer than for many operations. Meanwhile, quick action can sometimes save a struggling flap. If part of the flap is lost, staged repair is planned.
What is recovery like?
Recovery is long, since this is major, staged surgery. At first, a hospital stay with flap monitoring and catheter care is needed. Because the back donor site also heals, shoulder movement is built up gradually. Meanwhile, each stage brings its own recovery period. Full completion, including an implant, often takes a year or more.
How does it compare to metoidioplasty?
Metoidioplasty uses existing tissue, while this flap builds a larger phallus. The table sets out the difference.
| Feature | Metoidioplasty | Latissimus dorsi phalloplasty |
|---|---|---|
| Size | Smaller | Larger |
| Stages | Fewer | Several |
| Implant for erection | Not needed | Usually needed |
For wider counselling, reach our dedicated transgender health service. You may also read about metoidioplasty with vaginal preservation.
How do I begin at Elegance Clinic?
Begin with a private consultation with Dr. Ashutosh Shah in Surat, who assesses you and explains the stages. During that meeting, he sets out honest outcomes and provides a clear written estimate after examination. Because complex surgery like this may involve specialist input, the pathway is planned carefully. When ready, contact Elegance Clinic for a confidential appointment.
Note: This page is for general information and is not a substitute for a medical consultation. Gender affirming surgery is individualised, carries real risks, is often staged, and outcomes vary between people. Dr. Ashutosh Shah and the team will advise honestly what is appropriate for you.
Ready to Talk, Privately?
Book a confidential consultation with Dr. Ashutosh Shah. There is no pressure, only clear and honest guidance.